Updated on Apr 25, 2025 | COVID-19 Reflections, Featured, Research

Nicole Simons, MA, right, with Katherine Keller, Clinical Research Coordinator
When the first of several waves of COVID-19 cases hit New York City, Nicole Simons, MA, had just landed her first big job out of school as a research coordinator at the Icahn School of Medicine at Mount Sinai. In a matter of days, her dream job was eliminated, along with the jobs of several colleagues.
Then came the call from Human Resources: Could she take on a front-line job that would expose her to this unknown virus and clinics filled with COVID-19 patients? Her answer was a resounding yes.
In a moment of instant serendipity, she was reassigned to work for Alexander Charney, MD, PhD, a noted researcher in the field of schizophrenia, a disease that had first captured her attention in college.
Working closely with clinicians on the front lines during the pandemic would turn out to be a lifechanging experience. She visited hospital wards to collect samples, helped out staff when she could, and even served as a second author of a paper in Nature Medicine that described the team’s work. Now she is the Program Manager of the Jeff and Lisa Blau Adolescent Consultation Center for Resilience and Treatment and is a PhD student in the Clinical Research Program at the Icahn School of Medicine, with plans to continue research into the genetics of schizophrenia. “Working with clinical colleagues on the frontlines really got me thinking about how to narrow the gap between research and clinical care. I plan to use the lessons I’ve learned to keep building research programs that move us closer to becoming a true learning health care system.”
It’s a long way from those early days of the pandemic in 2020. Dr. Charney, Associate Professor, Psychiatry, and Genetics and Genomic Sciences, had been asked by hospital leadership to rapidly build up a COVID-19 Biobank that would collect hundreds of blood samples from patients hospitalized with COIVD-19. It would ultimately serve as a backbone for ongoing research into the virus and the human immune response.

Nicole Simons, MA
Dr. Charney’s team consisted of 100 volunteers who, like Ms. Simons, had seen their research projects paused but were given a chance to come help. The team quickly designed a sample-collection protocol, and once this was in place, the cadre of volunteers organized itself into six teams, with Ms. Simons assigned to the “Running Team.” This team was responsible for transporting collection kits to every location within the hospital, and then bringing those kits back.
What might sound like a simple and straightforward assignment involved a major hurdle. How to gain access to clinics where new hospital rules would not even allow families to enter, even when patients were seriously ill? Ms. Simons would have to find a way in.
“Entering those clinics was like entering a fog of war environment. The strain on the nurses and doctors was palpable; we needed to visit their clinics without creating additional work for them” she says. They had to figure out a way to make easy for them to know if they should allow the researchers on the floor.
“I came up with this idea of making our research team stand apart so we’d be instantly recognizable.” Her solution: hot pink everything. “We wanted to stand out, so we wore hot pink scrubs, gloves, hairnets. Even our labels were pink,” she says. She and her teammates quickly developed a rapport with the nurses managing the floors they’d visit at all hours of the day and night.
“I felt like we were on the outside looking in, that we were somehow protected bystanders while they provided round-the-clock, unconditional care for their patients. To say thank you and support them, we brought them candy and other treats,” she says. They heard that nurses working in the tents constructed in Central Park needed clean, dry socks, so they asked for sock donations, and the response was instantaneous.
Lending help to the clinicians working in the hardest of circumstances also perpetuated for her a sense of shared purpose with staff and faculty at Mount Sinai. Among the volunteers at the Biobank, she found strength.

During the pandemic, Nicole Simons, MA, left, and a team collected hundreds of blood samples from patients hospitalized with COIVD-19, working with MIriam Merad, MD, PhD, center, Dean for Translational Research and Therapeutic Innovation, and Alexander Charney, MD, PhD,
“We all shared this common goal to collect those samples, no matter the hurdles. When the hours were long, and the days were hard, we had this shared humanity that pulled us through,” she says.
When the team reached its goal of 500 samples, they pushed on, ultimately sampling more than 700 participants in 49 days, amounting to more than 10,000 vacutainers portioned into 50,000 smaller samples. A high level of organization was critical to success.
“But strong morale, in the darkest of times, was what really got us through those long days,” she says. “At such a difficult time, it felt like a huge stroke of luck to be working for Dr. Charney, a psychiatrist, leading the Biobank team. His commitment to resilience and mental health was non-stop. He created a safety net for us, with regular weekly check-ins and the option for one-on-one counseling with him any time.”
In July 2020, she served as second author of a paper published in Nature Medicine describing the Biobank’s unique 49- day deep dive to uncover the pathogenicity of the virus. The authors would describe their journey as “not necessarily a model to follow, but rather a live-and-learn memoir of our actions and mistakes under uniquely strenuous circumstances.”
“The team was working intensely in a very high stress, high stakes environment, without much preparation for what we would all come to realize was a once in a lifetime experience,” says Dr. Charney, now Director of The Charles Bronfman Institute for Personalized Medicine and Vice Chair of the Windreich Department of AI and Human Health. “Their mental health was front and center for me. What pulled them through, I believe, was their strong purpose and being part of the group that didn’t have to stay home.”
Updated on Mar 28, 2025 | COVID-19 Reflections, Featured
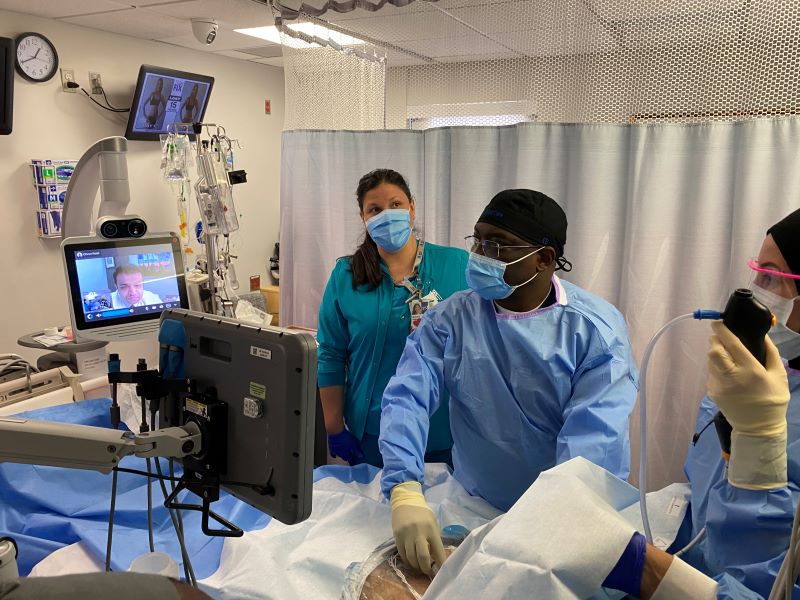
A tele-tracheostomy performed at the bedside in the Intensive Care Unit at Mount Sinai Queens Hospital on a patient who had been ventilated for respiratory failure.
It’s been five years since the COVID-19 pandemic’s first cases, and much has changed in the world of medicine. Virtual care, also known as telehealth, became routine, among other virtual adaptations such as iPad hook-ups to IV poles to connect families to say goodbye, and even Zoom classrooms.
A lesser-known adaptation, the tele-consult, allowing a doctor at one hospital to oversee and guide care at another hospital, came about as hospitals swelled with patients and doctors were spread thin.

Dhruv Patel, MD
Dhruv Patel, MD, Director of Quality and Associate Director of the Transplant Intensive Care Unit at The Mount Sinai Hospital within Mount Sinai’s Institute for Critical Care Medicine, was part of a team that helped to make this innovation possible.
In his role at the Institute, he oversees percutaneous tele-tracheostomies from his office at The Mount Sinai Hospital. A percutaneous tracheostomy is a minimally invasive procedure done with a needle that punctures the skin, which is performed at the bedside to create an opening in the windpipe to facilitate breathing.
“The capacity to beam into another hospital to oversee and guide a tracheostomy made a world of difference during the pandemic when we had large volumes of very sick patients on ventilators for prolonged periods,” says Dr. Patel.
“During the pandemic, we performed three times as many tracheostomies, as respiratory failure among infected patients became extremely common. This allowed for faster and less invasive bedside procedures, while avoiding the necessity to transfer critically ill and vulnerable patients to the operating room,” says Dr. Patel. The Institute has continued to train all critical care specialists to become proficient at performing bedside percutaneous tracheostomy.
Leveraging the tele-consult has presented an important training opportunity, says I. Michael Leitman, MD, FACS, Dean for Graduate Medical Education at the Icahn School of Medicine at Mount Sinai. Dr. Leitman, Professor of Surgery and Medical Education, oversees Mount Sinai’s resident training program, which is the largest in the county.
“The introduction of telemedicine and the ability now to do tele-consults at the bedside provides an important advantage for an attending to supervise residents and attending doctors as they round on critical, complex cases,” says Dr. Leitman.
Nazia Mashriqi, MD, MBA, ICCM Site Director at Mount Sinai Queens, performs approximately 30 tracheostomies annually.
“Even though we aren’t seeing many critical COVID-19 patients, we are still performing bedside percutaneous tracheostomies quite often for patients who require prolonged assistance of a mechanical ventilator for other respiratory illnesses, such as the flu or pneumonia. With Dr. Patel tele-consulting and present in the room as we perform these procedures, we can ensure a critical layer of oversight and safety,” says Dr. Mashriqi, who is also part of the Institute’s team. “The procedure is somewhat straightforward, but at the same time, proficiency is key to avoid complications of bleeding due to trauma to nearby tissues. We use multiple layers of visualization including ultrasound and bronchoscopy to enhance the safety of the bedside procedure,” says Dr. Patel, noting that the procedure is now rarely performed in the operating room.
Mount Sinai’s Institute for Critical Care Medicine oversees critical care at seven of Mount Sinai’s eight hospitals in New York, providing highly specialized, life-saving care for patients experiencing the most serious diseases and injuries, and those recovering from complex surgeries.
The Institute’s System Director, Roopa Kohli-Seth, MD, says the team provides care for more than 10,000 patients annually.
“Our critical care teams care for the sickest of patients at Mount Sinai’s hospitals, and the capacity to tele-consult and advise from afar has given us an important advantage in saving lives and ensuring both quality and safety. We see this as a great win for our patients and patient safety overall,” says Dr. Kohli-Seth.





